Understanding IBS Mixed Type: Symptoms, Gut Motility and What a Microbiome Test Can Reveal

IBS, Gut Motility and the Microbiome: Symptoms, Flare-Ups and Relief
IBS Mixed Type (IBS-M): Symptoms and How It Differs From Other Subtypes
Irritable bowel syndrome (IBS) is a common functional gut disorder. Functional means the gut usually looks structurally normal on standard tests, but the way it works — how it moves, senses and responds to its contents — is altered. IBS is diagnosed from symptom patterns rather than from a single laboratory result, which is why it is classified into subtypes.
What Is IBS Mixed Type?
IBS mixed type is the subtype used when bowel habits swing between constipation and diarrhoea. Classification is usually based on the Bristol Stool Form Scale and on how often each stool type occurs over recent months:
- IBS with constipation (IBS-C) is used when most abnormal stools are hard or lumpy.
- IBS with diarrhoea (IBS-D) is used when most abnormal stools are loose or watery.
- IBS mixed type (IBS-M) is used when hard and loose stools each make up a meaningful share of bowel movements — commonly described as more than a quarter of them.
- Unclassified IBS (IBS-U) is used when the pattern does not meet either threshold.
The label can change over time. Someone whose symptoms shift from a mainly constipating pattern to a mainly loose one may move between subtypes, which is one reason management for IBS-M often needs to be adjusted rather than fixed.
Symptoms People With IBS-M Commonly Report
- Abdominal pain or discomfort, often eased by a bowel movement
- Alternating constipation and diarrhoea, sometimes within the same week
- Bloating, distension and excess wind
- Urgency and a sudden need to find a toilet
- A feeling of incomplete evacuation
- Symptoms that flare around stress, large meals, travel or hormonal changes
Pain and changes in bowel habit are the core features. Bloating is common but is not required for a diagnosis.
Why IBS-M Can Be Harder to Manage
Because the bowel pattern moves in both directions, a treatment that helps one phase can worsen the other. A laxative that relieves a constipated stretch may contribute to diarrhoea days later, and an antidiarrhoeal taken during a loose stretch may tip things back towards constipation. Clinicians therefore tend to work stepwise, adjusting to whichever pattern is dominant at the time. Understanding gut motility and the gut microbiome can make that process more informed.
How the Gut Microbiome Fits In
The gut microbiome is the community of bacteria, archaea, fungi and viruses living in the digestive tract. Research consistently finds differences in the composition and metabolic activity of the gut microbiota in some people with IBS compared with people without it, and these differences have been associated with changes in gut motility, gut barrier function and pain signalling.
That makes the microbiome a reasonable area to explore when symptoms persist — but as one part of the picture, not the whole answer.

Gut Motility and IBS Mixed Type: Why Transit Speed Fluctuates
Gut motility is the coordinated muscular activity that moves food, fluid and waste through the digestive tract. It includes peristalsis, the wave-like contractions that propel contents forward, and segmentation, the local contractions that mix contents with digestive juices. Transit time describes how long material takes to travel through the gut.
How Motility Relates to IBS-M
Motility is regulated by the enteric nervous system (the gut's own nerve network), signals from the brain and spinal cord, hormones and local chemical messengers. When transit speeds up, there is less time for water to be absorbed, stools become loose and urgency increases. When transit slows, more water is absorbed and stools become hard and difficult to pass. IBS-M reflects unstable regulation rather than a consistently fast or slow gut.
Motility alone does not explain IBS pain. Visceral hypersensitivity — a lower threshold for perceiving normal stretch and pressure in the gut — is thought to amplify sensations, which is why pain intensity and bowel habit do not always match.
What Influences Gut Motility
- Fibre type and amount, and how much fluid you drink
- Meal size, fat content and how regularly you eat
- Physical activity and sedentary time
- Stress and sleep quality, through the brain-gut axis
- Medications, including opioids, iron supplements, some antidepressants and calcium channel blockers
- Hormonal shifts, including the menstrual cycle and thyroid function
- Microbial metabolites such as short-chain fatty acids and bile acids
- Pelvic floor function, including uncoordinated defecation
How Microbes Influence Motility
Gut bacteria ferment fibre and other substrates into short-chain fatty acids including butyrate, propionate and acetate. These compounds feed the cells lining the colon, influence gut barrier function, interact with the nervous system and affect how quickly contents move. Bile acid metabolism by gut bacteria also influences secretion and transit, and methane produced by certain archaea has been associated with slower transit and constipation-type patterns, while hydrogen patterns have been linked with faster transit in some studies.
This remains an area of active research rather than settled clinical practice. Associations between specific microbes or metabolites and IBS symptoms have been reported, but they are not yet reliable enough to diagnose IBS or to predict which treatment will work for an individual.
What a Microbiome Test Can and Cannot Tell You
A stool-based microbiome test can describe which groups of microorganisms are present, estimate diversity and, depending on the panel, measure markers such as faecal calprotectin or short-chain fatty acids. That can be genuinely useful context.
A microbiome test cannot confirm or exclude IBS, which remains a symptom-based diagnosis, and it cannot rule out other conditions that produce similar symptoms. Results reflect one sample at one point in time and are influenced by diet, medication, recent illness and how the sample was collected. They are best read alongside your symptoms and, where relevant, with a clinician.

IBS, Gut Motility and the Microbiome: Symptoms, Flare-Ups and Relief
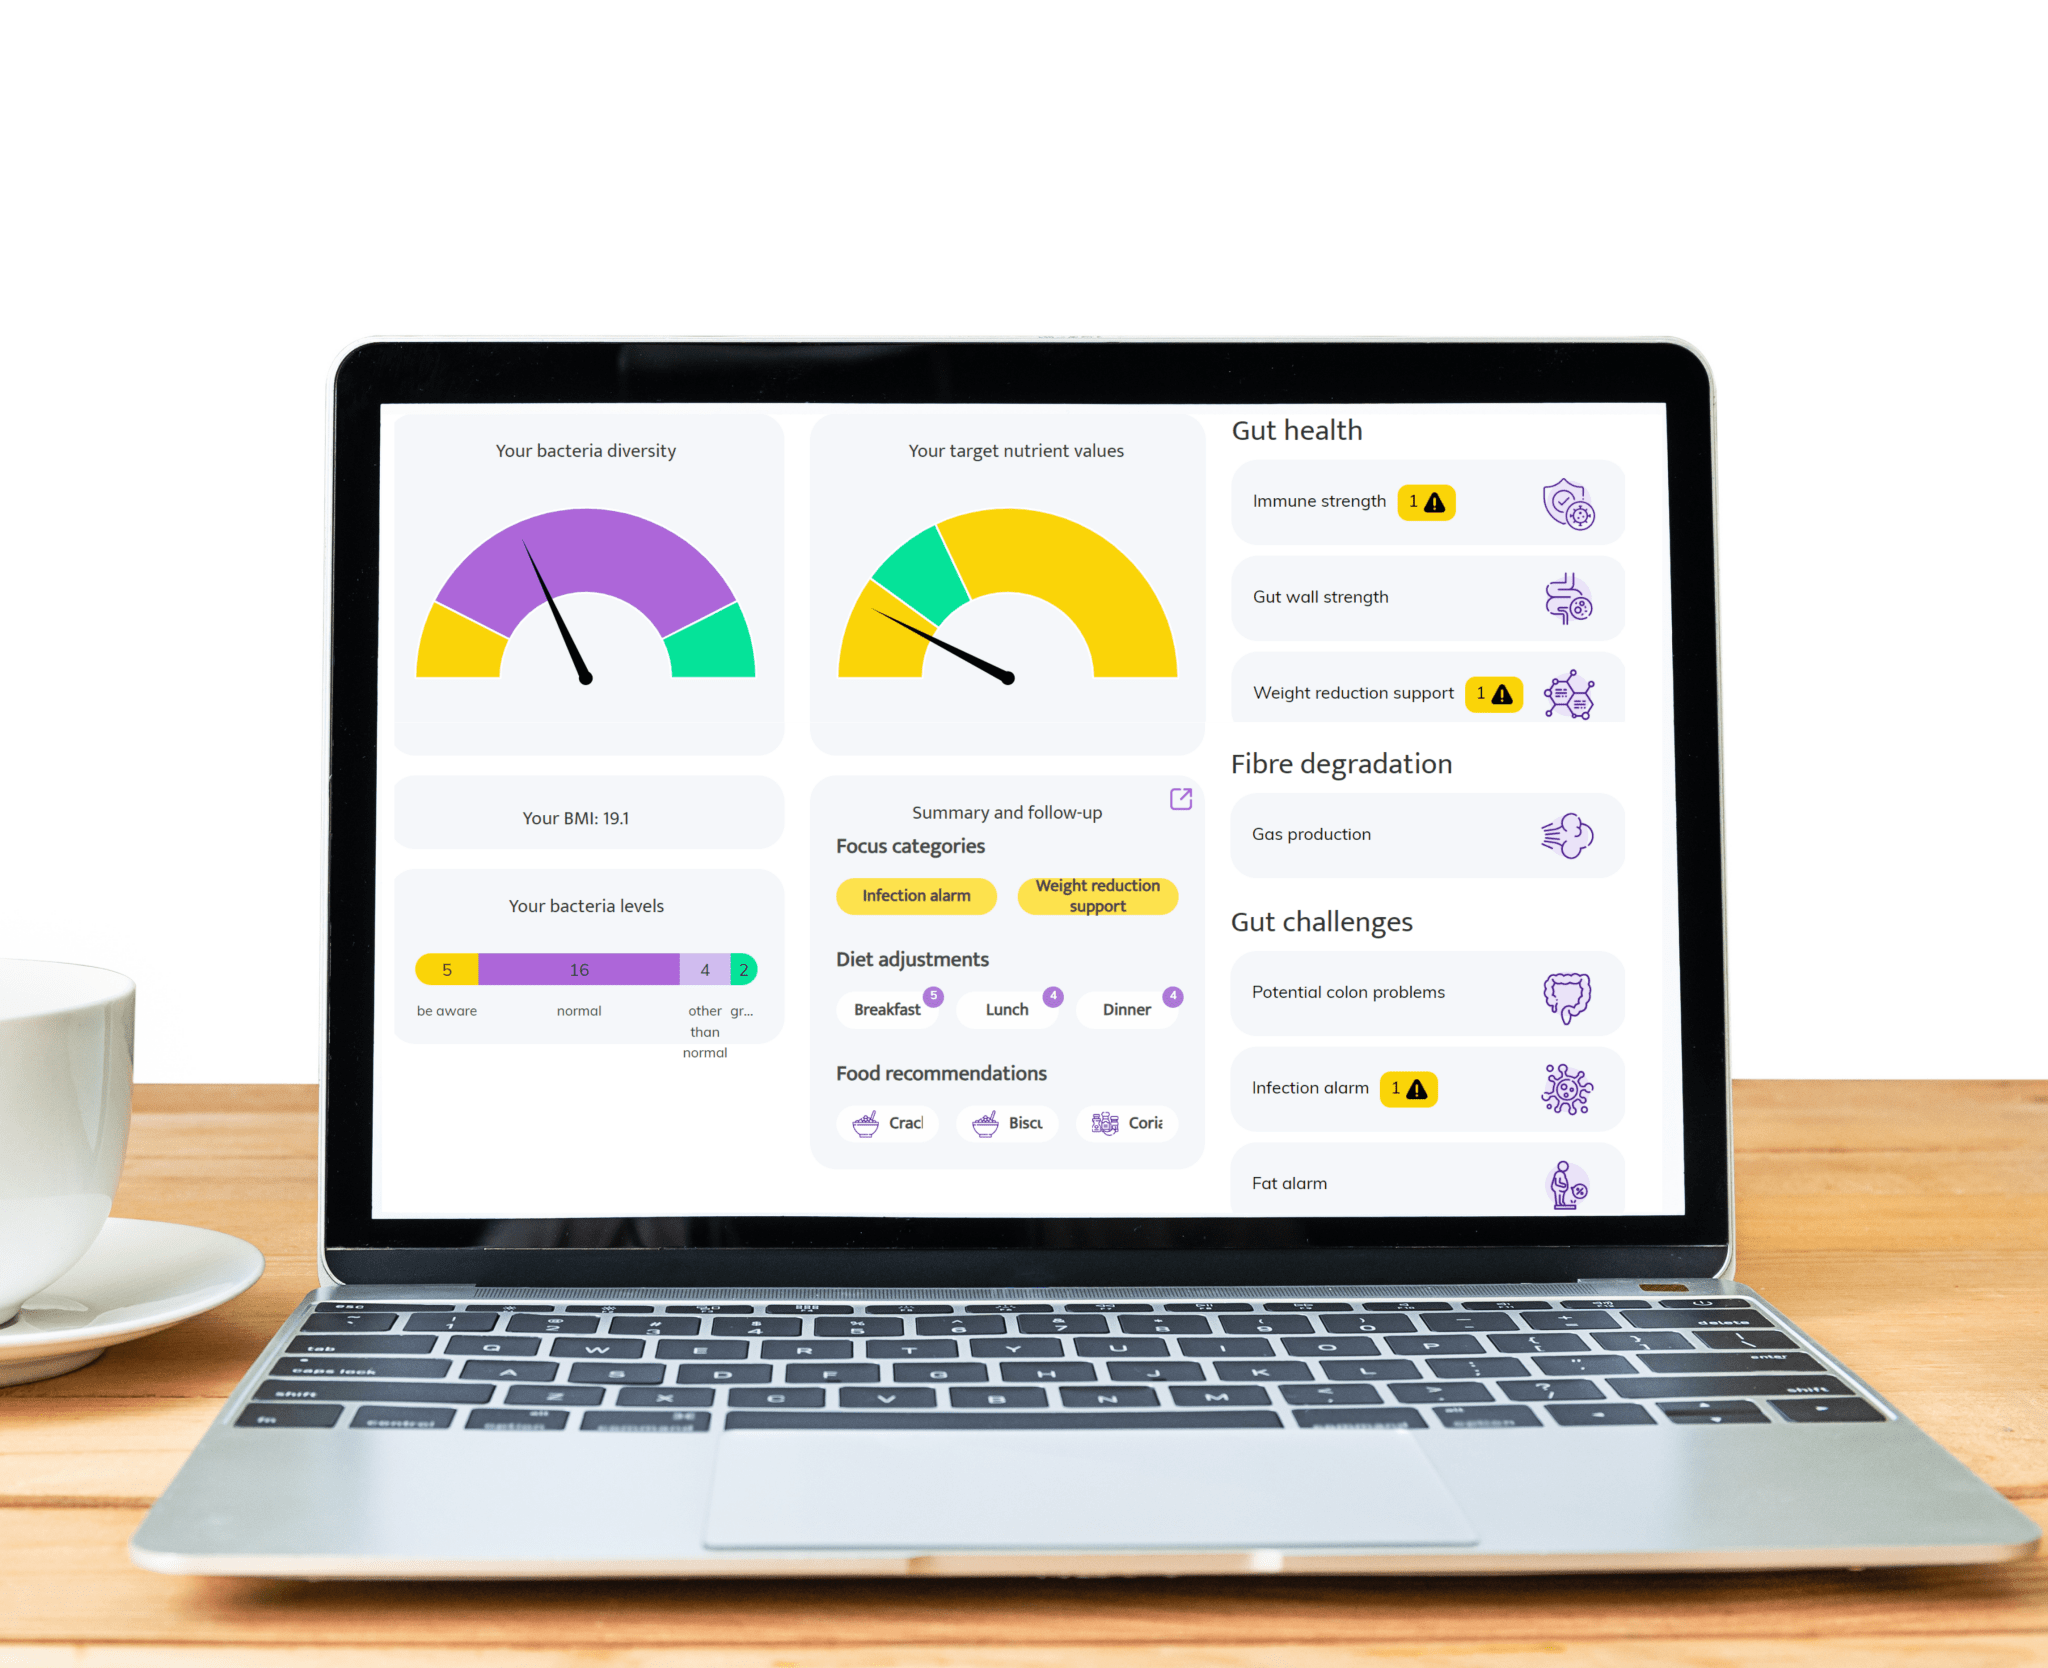
What a Comprehensive IBS Mixed Type Gut Test Looks At
Sample Collection and Technology
Most gut microbiome tests are done at home using a stool sample collected in a sterile kit and returned for laboratory analysis. The technologies used vary:
- 16S ribosomal RNA gene sequencing identifies broad bacterial groups and estimates relative abundance and diversity.
- Shotgun metagenomics sequences a wider range of microbial DNA and can provide species-level detail as well as information about microbial functions and pathways.
- Targeted panels use qPCR to look for specific organisms or markers.
- Biomarker assays such as faecal calprotectin measure inflammation-related proteins.
- Metabolite panels estimate short-chain fatty acids and other microbial products.
Breath tests for hydrogen and methane are sometimes used alongside stool testing, but they measure something different: gases produced after a test sugar, not the microbiome itself.
What the Results Typically Describe
- Diversity. Higher diversity is generally considered a feature of a more resilient gut community. Lower diversity has been reported more often in people with IBS, although the overlap between individuals with and without symptoms is substantial.
- Key microbial groups. Reports may comment on short-chain-fatty-acid producers such as Faecalibacterium prausnitzii, on Bifidobacterium and Lactobacillus, or on groups that can behave opportunistically. Lower levels of some beneficial groups have been associated with more bothersome symptoms in some studies.
- Inflammatory markers. A raised faecal calprotectin is not expected in IBS and usually points towards investigating inflammation more thoroughly, which is one reason stool testing can help separate IBS from inflammatory bowel disease.
- Microbial metabolites. Butyrate, propionate and acetate, together with bile acid transformations, are among the clearest links between the microbiome and gut function, and they are plausible contributors to both motility and pain signalling.
How to Read Results Without Over-Interpreting Them
Microbiome results are descriptive, not diagnostic. A high or low value for one group rarely maps neatly onto one symptom, and reference ranges differ between laboratories. Interpretation is most useful when it is combined with your symptom history, medication use, diet and any prior medical assessment. An unusual-looking result is not automatically a problem, and a normal-looking result does not mean your symptoms are not real.
Who May Find Testing Useful
Testing tends to be most informative for people with persistent, well-characterised symptoms who want to track changes over time, or who are planning dietary or supplement changes with a practitioner and want a baseline. It is less useful as a first step. If you have warning signs such as blood in the stool, unexplained weight loss or symptoms that wake you at night, medical assessment comes first — see the section below.
Managing IBS Mixed Type: Evidence-Informed Options
There is no single treatment that resolves IBS-M. Guidance generally favours a stepwise approach that starts with diet and lifestyle, adds targeted supplementation where appropriate and reserves medication for symptoms that remain bothersome. Because IBS-M alternates, plans often need adjusting to whichever pattern is dominant at the time.
Diet and Fibre
- Soluble fibre such as psyllium is one of the most commonly recommended first steps and can help with both hard and loose stools. Insoluble fibre such as wheat bran helps some people but can worsen bloating and wind in others.
- The low-FODMAP diet has the strongest dietary evidence in IBS. It works best as a short, structured trial with a dietitian followed by planned reintroduction, rather than as permanent restriction.
- Regular meals, adequate fluid intake and moderation of caffeine and alcohol can reduce symptom swings.
- Food triggers are individual. Keeping a simple symptom and food diary for a few weeks is often more useful than eliminating many foods at once.
Probiotics and Targeted Supplements
Probiotic evidence in IBS is mixed and strain-specific. Some combinations have been associated with modest improvements in global symptoms, bloating or abdominal pain, while others have shown little benefit. Response varies between individuals and there is no reliable way to predict who will respond. Postbiotics such as butyrate supplements are an active area of research, with evidence still limited.
Medication Options
Medication for IBS-M is usually discussed with a clinician, because the alternating pattern makes timing important:
- Antispasmodics, including peppermint oil, may ease cramping and pain.
- Antidiarrhoeals such as loperamide can be used during loose phases, but may worsen constipation.
- Osmotic laxatives such as polyethylene glycol are used during constipation phases.
- Low-dose neuromodulators, including certain tricyclic antidepressants or SSRIs, are sometimes prescribed for persistent pain.
- Antibiotics such as rifaximin are used in some diarrhoea-predominant cases, and other agents may be considered depending on the dominant symptom.
This is not a complete list, and none of these options should be started without medical advice.
Brain-Gut Behavioural Approaches
Because the brain-gut axis strongly influences motility and pain perception, psychological approaches have a solid evidence base in IBS. Gut-directed hypnotherapy and cognitive behavioural therapy have both been studied for symptom relief. Improving sleep, building regular movement into the day and reducing sustained stress may also help, even when they do not target the gut directly.
Tracking Progress
A short symptom diary recording stool pattern, pain, bloating and possible triggers can make reviews with a clinician far more productive. Repeat microbiome testing is worth doing only when the result would change a decision — for example, when assessing whether a dietary change has shifted your gut community. Testing more often than that adds cost without adding clarity.

When to See a Doctor About IBS-Like Symptoms
IBS itself does not damage the gut and is not known to increase the risk of cancer. But IBS is diagnosed from symptoms, and several other conditions produce symptoms that overlap with it. That is why a medical review matters, particularly when warning signs are present.
Six Signs Your Gut May Need Medical Attention
- A lasting change in bowel habits, especially if it has persisted for several weeks or is new for you
- Blood in the stool, or black, tarry stools
- Unexplained weight loss or loss of appetite
- Symptoms that wake you from sleep, or that are steadily getting worse
- Persistent vomiting, difficulty swallowing, or a new lump or swelling in the abdomen
- Fatigue, paleness or other signs of anaemia, or a family history of bowel or ovarian cancer
These features do not mean that something serious is present, and most of the time it is not. They are simply reasons to be assessed rather than to manage symptoms alone.
Conditions That Can Overlap With IBS
- Inflammatory bowel disease such as Crohn's disease or ulcerative colitis
- Coeliac disease
- Bile acid malabsorption
- Small intestinal bacterial overgrowth
- Thyroid dysfunction
- Pelvic floor dysfunction or uncoordinated defecation
- Gynaecological conditions that cause pelvic pain and bloating
- Some cancers, which are far less common but can produce overlapping symptoms
Blood tests, stool tests and, where appropriate, imaging or endoscopy can help distinguish these. A microbiome test does not replace that assessment.
Keeping Expectations Realistic About Microbiome Testing
A gut microbiome test is a description of a sample, not a diagnosis. Results can change with diet, medication, illness and time, and reference ranges vary between laboratories. Used well — as a baseline, as a tracking tool or as a way to guide a diet or supplement trial with a practitioner — it can add useful structure to what is often a frustrating process. Used as a standalone answer, it tends to raise more questions than it resolves.
Frequently Asked Questions
What is the best treatment for mixed IBS?
There is no single best treatment. Guidance favours a stepwise, individualised plan: begin with diet and lifestyle measures such as soluble fibre, regular meals and, where suitable, a supervised low-FODMAP trial; add probiotics if they appear to help; and use medication aimed at whichever pattern is dominant, alongside brain-gut approaches such as gut-directed hypnotherapy or CBT for pain. What works is usually found by tracking symptoms over weeks and adjusting with a clinician.
How do you fix poor gut motility?
It depends on which direction motility has gone wrong. For slow transit, useful steps often include adequate fluid, soluble fibre, regular physical activity, predictable meal times and, where appropriate, osmotic laxatives or pelvic floor physiotherapy for uncoordinated defecation. For fast transit, reducing triggers such as large fatty meals and excess caffeine and using antidiarrhoeals under guidance may help. Reviewing medications that speed up or slow down the gut matters too, because several common prescriptions affect transit.
What cancers can mimic IBS?
Colorectal (bowel) cancer and ovarian cancer are the two most often mentioned, because both can cause abdominal pain, bloating and changes in bowel habit. IBS does not cause cancer, and cancer is a much less common explanation for these symptoms. Warning signs such as blood in the stool, unexplained weight loss, anaemia or symptoms that wake you at night should prompt medical assessment rather than further self-experimentation.
Find more details about IBS & Motility
You can find more information on the related topics below.
Read more: IBS mixed type, gut motility and what microbiome testing can show
Your Gut Has a Story. Read It — Then Fix Potential Problems
Full microbiome sequencing + Gut Health Index. Metabolic pathways, diversity, keystone species. Personalized plans available (diet, supplements, diary, recipes). EU lab + Maastricht University spin-off + GDPR-safe.