Stool Tests for Diarrhea and IBS: Purpose, Types, Preparation and Results

IBS, Gut Motility and the Microbiome: Symptoms, Flare-Ups and Relief
Stool Test 101: Purpose, Symptoms and What Testing Can Reveal
A stool test is a laboratory analysis of a stool sample. It can look for infection, inflammation, hidden blood, malabsorption, pancreatic enzyme insufficiency and shifts in the gut microbiome. That makes it useful when persistent diarrhea, cramping, urgency, bloating or a change in bowel habit needs to be investigated. Rather than assuming every loose stool is IBS, stool testing helps narrow down what is driving symptoms and whether a treatable cause is present.
Why Ongoing Diarrhea Is Not One Condition
Loose, frequent stools can reflect several different mechanisms. An infection, an inflammatory bowel condition, a malabsorption problem, pancreatic enzyme insufficiency or a disorder of gut-brain interaction such as irritable bowel syndrome (IBS) can all present in similar ways. Because the overlap is considerable, laboratory evidence is often needed to separate these possibilities.
What a Stool Test Can Look For
A routine stool test usually combines a physical and chemical check with microscopy, and adds culture or specific assays when a particular cause is suspected. Depending on the test ordered, stool can reveal:
- Blood that is not visible to the eye (occult blood)
- Bacteria such as Salmonella, Shigella, Campylobacter, Yersinia, E. coli O157 and Clostridioides difficile
- Parasites and their eggs or cysts, including Giardia lamblia, Cryptosporidium and Entamoeba histolytica
- Viruses such as norovirus and rotavirus, usually detected with molecular testing
- Inflammatory markers such as calprotectin and lactoferrin
- Digestive markers such as fecal elastase and fat content, which can indicate pancreatic insufficiency or malabsorption
- Indicators of fermentation and bile acid handling, such as short-chain fatty acids
What Stool Testing Cannot Do
A stool test is one part of a clinical picture rather than a diagnosis on its own. No stool test currently diagnoses IBS, which remains a clinical diagnosis based on symptom patterns and the exclusion of other conditions. Microbiome sequencing is a developing field: results describe patterns that require interpretation alongside symptoms and history, and their clinical meaning is not always clear. A normal result is also not absolute proof that nothing is wrong, because a single sample can miss intermittent bleeding, low-level infections or parasites.
The Gut Microbiome and Motility in IBS
IBS is characterized by recurrent abdominal pain and a change in bowel habits, including diarrhea-predominant IBS (IBS-D). Its causes are not fully understood, but research points to an interaction between the gut microbiome, gut motility, immune signaling and the nervous system.
The gut microbiome is the community of bacteria, viruses, fungi and other microorganisms living in the digestive tract. In some people with IBS, studies have found patterns of dysbiosis, meaning a shift in microbial diversity and composition, including lower relative abundance of groups such as Bifidobacterium and Lactobacillus and higher levels of other organisms. These patterns have been associated with increased gut permeability, low-grade inflammation and altered motility, although the relationship appears to work in both directions and is still an active area of research.
Gut motility refers to the coordinated muscle contractions that move contents through the digestive tract. Faster transit tends to produce loose and frequent stools, while slower transit contributes to constipation. Microbiome composition, inflammatory mediators and the enteric nervous system can all influence transit speed, which is why assessing motility alongside microbial patterns can be useful.

Types of Stool Tests: What Each One Detects
The term stool test is an umbrella term for several laboratory methods. Each answers a different question, and they are frequently combined. Stool tests may also be called stool sample tests, fecal tests, stool analysis, or by the specific method ordered, such as stool culture, ova and parasite exam, fecal immunochemical test (FIT) or fecal occult blood test (FOBT).
For practical purposes, they fall into two broad groups: tests used to investigate symptoms such as diarrhea, and screening tests used to look for hidden blood or altered DNA in people without symptoms. A simple way to think about the three main categories is infection testing, inflammation and digestive function markers, and colorectal cancer screening tests.
Stool Culture
A stool culture attempts to grow live bacteria from the sample on selective media so they can be identified. It is most useful when bacterial gastroenteritis is suspected.
- Typically detected: Salmonella, Shigella, Campylobacter, Yersinia and E. coli O157, while Clostridioides difficile is usually identified through toxin or molecular testing instead
- Added value: the isolated organism can be tested for antibiotic susceptibility, which molecular methods generally cannot do
- Turnaround: cultures commonly take around 24 to 72 hours, and longer when slow-growing or unusual organisms need further work
- Limitations: not every organism grows easily, recent antibiotic use can suppress growth, results depend heavily on sample quality, and cultures do not assess viruses or most parasites
The difference between a stool test and a stool culture is straightforward: a stool test is any laboratory analysis of a stool sample, while a stool culture is one specific method within that category that tries to grow and identify living bacteria.
Molecular Stool Tests (PCR Panels)
Multiplex PCR panels detect genetic material from many bacteria, viruses and parasites in a single run. They are fast, often reported within hours to a day, and highly sensitive. The trade-off is interpretation: a positive result shows that DNA from the organism is present, but not necessarily that it is alive, that it is causing symptoms or which antibiotic would be effective against it.
Antigen and Toxin Tests
These targeted tests detect specific proteins produced by an organism or by the gut in response to it. Examples include Giardia antigen, Helicobacter pylori antigen and Clostridioides difficile toxin testing. They are quick, relatively inexpensive and useful when a specific cause is already suspected.
Occult Blood Tests: gFOBT, FIT and Stool DNA
These tests look for blood in stool that cannot be seen. The guaiac-based fecal occult blood test (gFOBT) uses a chemical reaction, while the fecal immunochemical test (FIT) uses antibodies that recognize human hemoglobin and is generally preferred because it requires fewer dietary restrictions. Stool DNA tests combine FIT with markers of altered DNA.
Occult blood tests are used mainly for colorectal cancer screening in people without symptoms. They are not designed to explain chronic diarrhea or to evaluate IBS. A positive result means blood was detected, and the source could be polyps, inflammation, hemorrhoids, an ulcer or a tumor, which is why a positive result is usually followed up with colonoscopy. Blood in stool is not automatically cancer, but it always deserves assessment.
Inflammation and Digestive Function Markers
Calprotectin and lactoferrin give an estimate of neutrophil-driven inflammation in the gut. Raised values may prompt further assessment for inflammatory bowel disease, although they can also rise with infection. Fecal elastase and stool fat measurement assess pancreatic enzyme output and fat absorption, which helps identify malabsorption as a contributor to diarrhea.
Microbiome Sequencing and Motility Markers
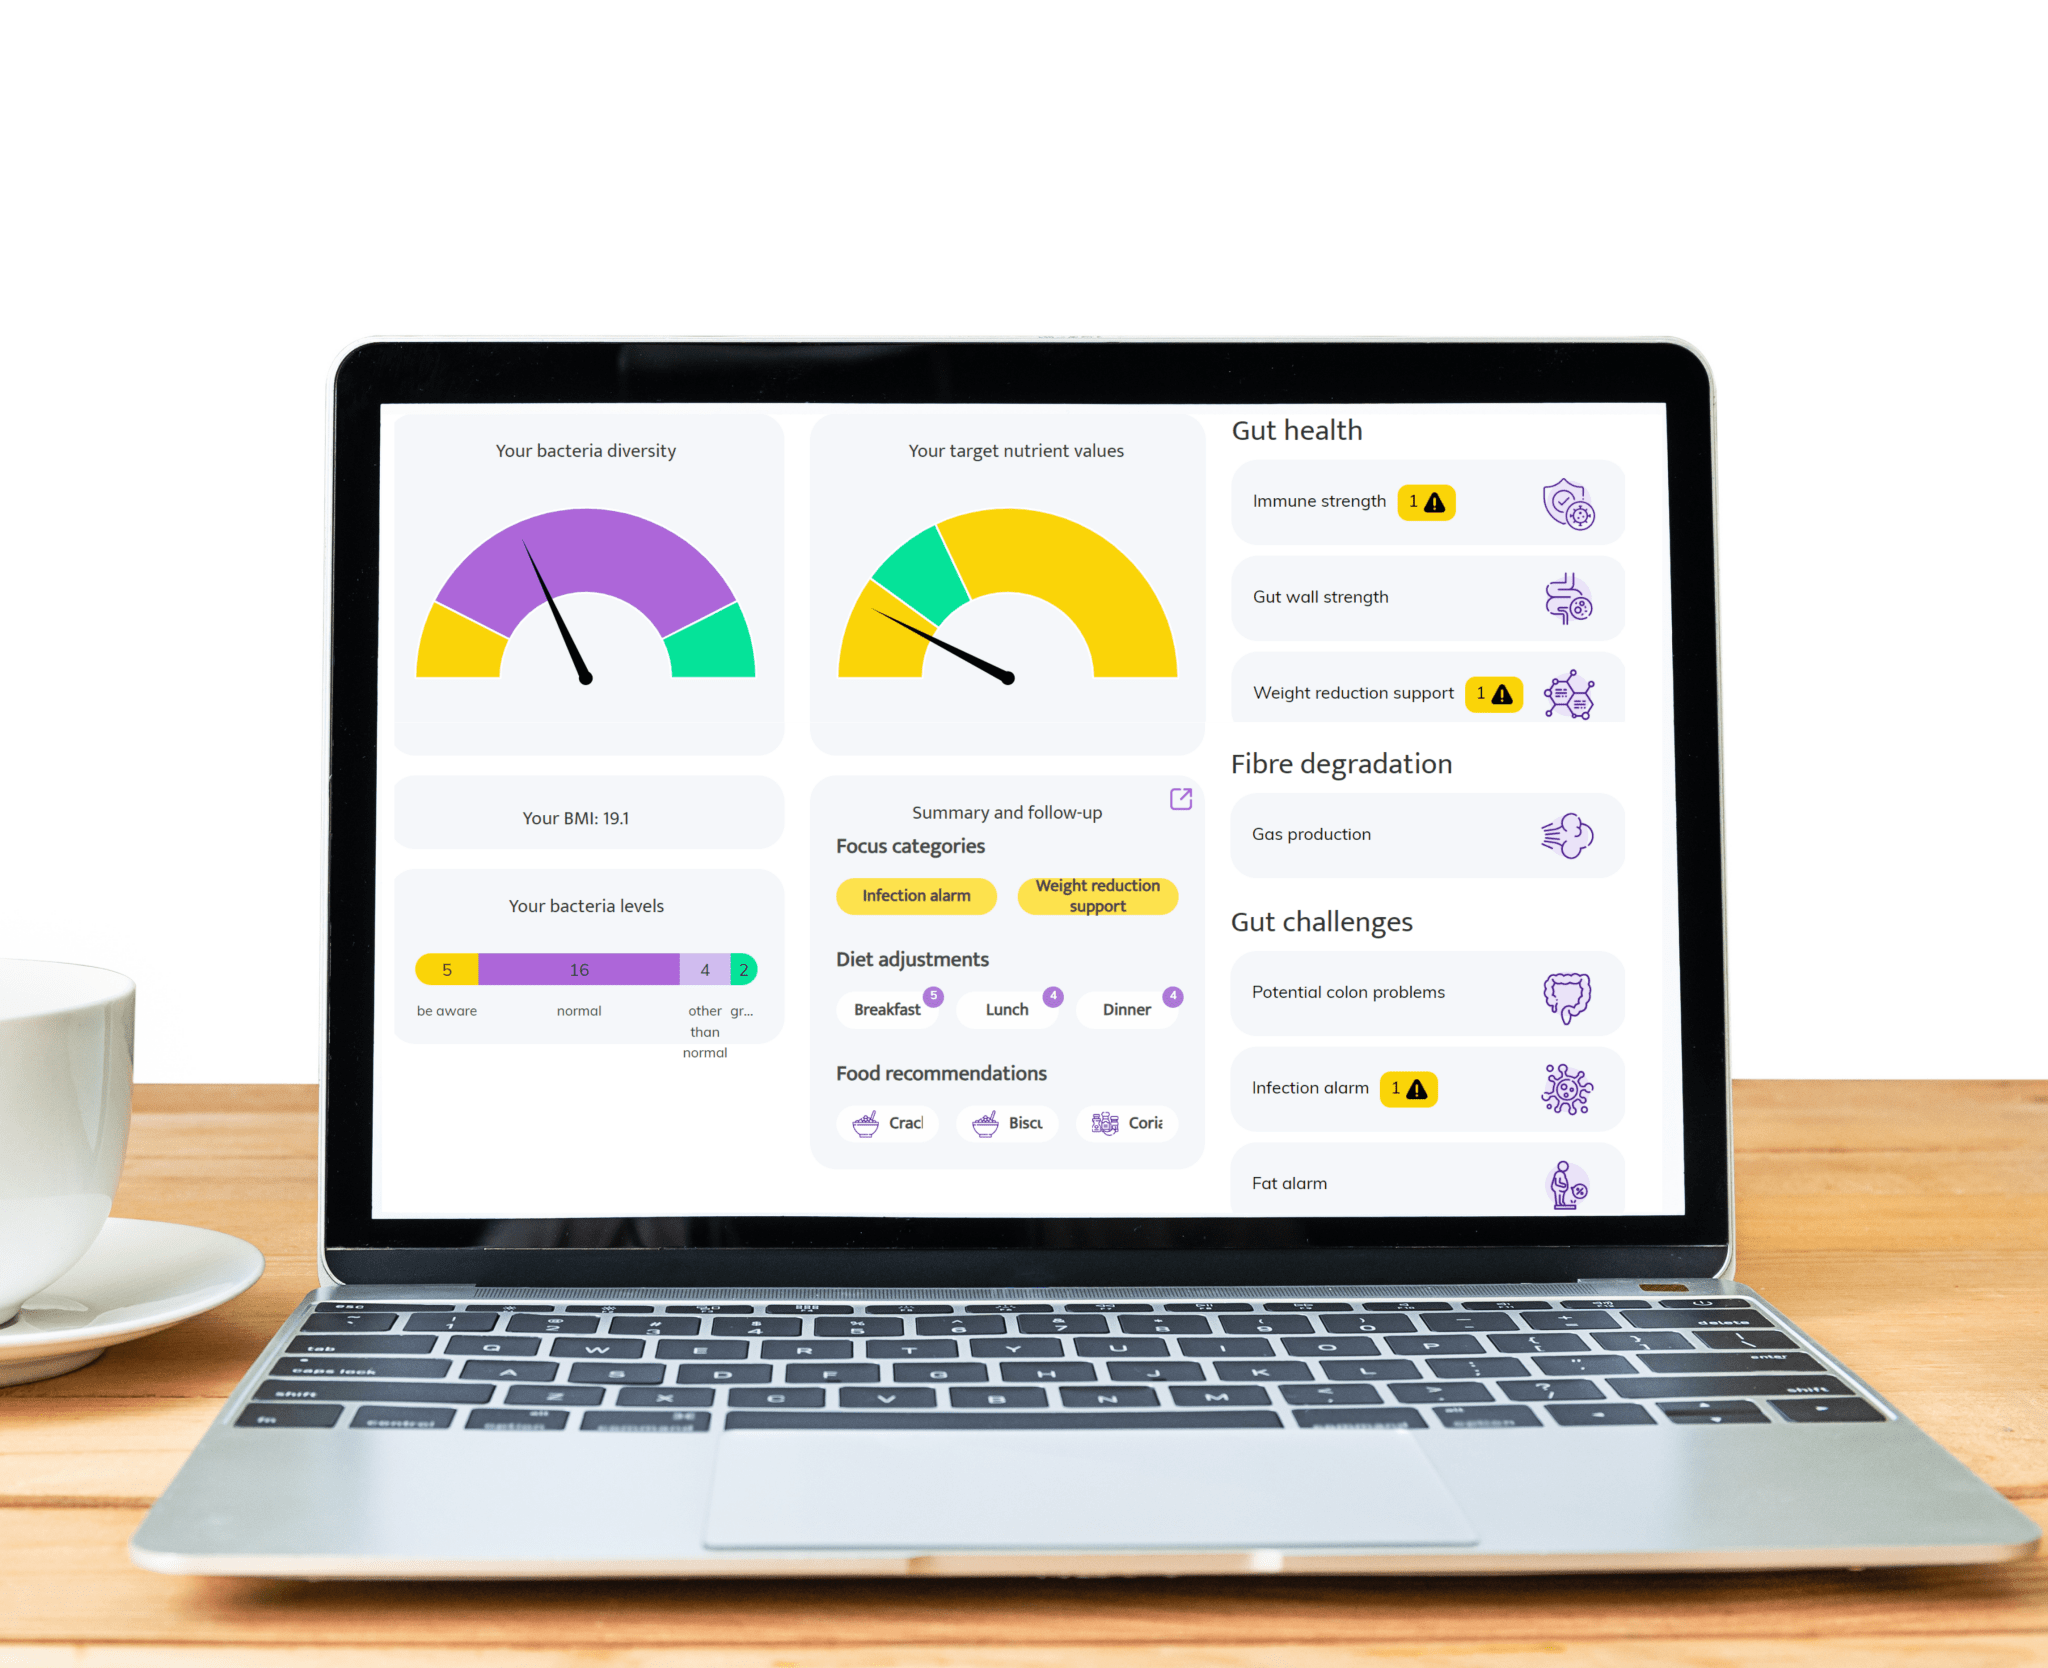
16S rRNA gene sequencing profiles bacterial populations, usually to genus level, while shotgun metagenomics can provide species-level and functional information. Alongside these, markers such as short-chain fatty acids (including butyrate and propionate) and bile acid profiles offer indirect insight into fermentation and transit speed, since altered fermentation and bile acid handling have been associated with diarrhea-predominant symptoms.
It is worth treating these results as descriptive rather than diagnostic. Microbial communities vary between individuals and over time, and the field is still evolving, so sequencing findings are best interpreted by a clinician alongside symptoms, diet and other test results.

IBS, Gut Motility and the Microbiome: Symptoms, Flare-Ups and Relief
How to Prepare for a Stool Test and Collect a Sample
Preparation depends entirely on which test is being done. Many stool tests need no fasting and no special diet, but certain instructions are commonly given and are worth following carefully. Always follow the written instructions supplied with your kit or given by your clinician, because these vary between laboratories and test types.
What to Avoid Before a Stool Test
- Some medications may need to be paused temporarily, including antibiotics, antidiarrheal medicines, antacids and iron supplements, but only if your clinician advises it.
- Large doses of vitamin C, including supplements and citrus, can interfere with some occult blood tests.
- For a guaiac-based occult blood test, red meat and raw or lightly cooked vegetables and fruits such as broccoli, radish, turnip, horseradish and melon are often avoided for a few days beforehand, because they can cause false positives with the chemical method.
- NSAIDs such as aspirin and ibuprofen may be paused if advised, as they can irritate the gut lining and produce traces of blood.
- Collecting a sample during menstruation is usually avoided for occult blood testing, as it can contaminate the sample.
Step-by-Step: How to Collect a Stool Sample
- Use the collection container, gloves and collection paper provided in the kit.
- Collect the sample onto clean, dry paper or a collection sheet rather than from the toilet bowl.
- Take small amounts from several different parts of the stool to represent the whole sample, and include any areas that look bloody, mucousy or unusually loose.
- Avoid contact with urine, toilet water and toilet paper.
- Seal and label the container as instructed, and store it as directed, usually refrigerated rather than frozen if it will not be returned straight away.
- Return or ship the sample within the timeframe given, using any cold packs or transport medium supplied.
Collecting a Stool Sample from a Child
Stool tests are sometimes ordered for children with diarrhea, constipation, abdominal pain, mucus in the stool or suspected infection. The same basic principles apply, but a few practical points can make collection easier. Use a clean potty liner or collection paper rather than letting the sample mix with urine or toilet water, and transfer a small amount into the container with the spoon or stick provided. Keep the sample cool and return it as quickly as the laboratory requests.
Seek medical advice for a child's stool if there is blood, black or tarry stool, persistent vomiting, fever, severe pain, signs of dehydration, diarrhea lasting more than a few days, or if a baby is unusually sleepy or not feeding. These signs do not automatically mean something serious, but they change how quickly a child should be assessed. For constipation, warning signs can include severe pain, vomiting, a swollen abdomen, blood in the stool, or a child who is not passing stool or gas at all.
How Fresh Does the Sample Need to Be?
Freshness matters a great deal, particularly for culture, parasite detection and microbiome analysis, where live organisms or fragile genetic material are being examined. Many laboratories ask for samples to arrive within a few hours to 24 to 48 hours, while kits that use preservative or transport media can extend that window. A sample older than the stated limit may produce unreliable results, so follow the kit's own instructions rather than an approximate rule.
What to Expect
A stool test involves no needles and no discomfort, because you collect the sample yourself at home or in a clinic. The variation lies in logistics: whether one sample is enough or three samples on different days are needed for parasite or occult blood testing, and how quickly the sample must reach the laboratory.
Understanding Stool Test Results
A positive stool test does not automatically mean a disease, and a negative result does not always rule one out. Results are interpreted alongside symptoms, medical history, medication use and, when relevant, other tests. The meaning depends on the marker being measured.
How to Read a Stool Examination Report
A normal stool report generally shows no detectable blood, no significant pathogens or parasites, unremarkable microscopy and inflammatory markers within the laboratory's reference range. Reports differ in layout, and reference ranges vary between laboratories, so the ranges printed on your own report are the ones to use.
Small differences on a report are not automatically meaningful. A value just outside the reference range may be a normal variation, may reflect diet, recent medication or the timing of the sample, or may be the first signal of something worth investigating further. This is why results are interpreted together with your symptoms and medical history rather than in isolation.
Microbial Profiles and Dysbiosis
When sequencing or culture is included, clinicians look for decreased beneficial groups such as Bifidobacterium, Lactobacillus and Faecalibacterium prausnitzii, and for increases in opportunistic or pathogenic organisms such as Clostridioides difficile and some Escherichia coli strains. Higher-than-expected yeast counts, for example Candida, may also be noted. These patterns can be useful, but they describe association rather than proof of cause.
Inflammatory Markers and Immune Responses
Elevated calprotectin or lactoferrin suggests neutrophil-driven inflammation and may prompt further investigation for inflammatory bowel disease or infection. Raised fecal secretory IgA can reflect mucosal immune activation, which has been described in IBS and in some food-related reactions, although it is not specific to any single condition.
Digestive Function and Absorption
Low fecal elastase may indicate pancreatic insufficiency, which can sometimes be managed with enzyme support. Raised stool fat suggests malabsorption and is one of the recognized contributors to chronic diarrhea. Recognizing these patterns early can prevent symptoms from being attributed to IBS alone.
Motility and Fermentation Indicators
Short-chain fatty acid profiles showing low butyrate may suggest altered fermentation, which affects the cells lining the colon as well as motility. Abnormal bile acid handling has been associated with accelerated transit and watery stools, and in some cases responds to bile acid-binding medication. These markers are supportive rather than definitive, and are usually interpreted alongside symptom patterns.
What a Positive Result Means
A positive result means the specific marker the test was looking for was detected, which is not the same as a diagnosis. A positive culture means a potentially harmful bacterium grew; a positive occult blood test means blood was found and a source needs to be identified; a positive calprotectin means inflammation is likely present. Each type of positive result has its own meaning and its own recommended next step, which your clinician will explain in the context of your symptoms.
If a Stool Culture Is Negative but Diarrhea Continues
A negative culture does not explain all diarrhea. Cultures only look for certain bacteria, and they can miss viruses, parasites, inflammation, malabsorption, bile acid problems and functional causes such as IBS. If diarrhea continues, the next step is usually a broader review of symptoms, medication and diet, with additional tests chosen based on the pattern of illness rather than repeating the same culture automatically.
Putting Stool Test Results into Practice
Results are a starting point for a conversation with a qualified clinician, not a treatment plan on their own. Which findings appear usually determines which approaches are worth trying first, and in what order.
Dietary Adjustments
- A structured low FODMAP trial, ideally with a planned reintroduction phase rather than indefinite restriction
- Removing specific suspected triggers identified from symptom history and test findings
- Choosing fiber types deliberately, since soluble fibers help some people with diarrhea-predominant symptoms while highly fermentable fibers can worsen bloating
- Addressing nutritional gaps or supporting digestion when enzyme insufficiency or malabsorption is suspected
Probiotics, Prebiotics and Targeted Supplementation
Where testing suggests low relative abundance of certain beneficial groups, a clinician may suggest specific probiotic strains or prebiotic fibers. Evidence varies considerably by strain, dose and symptom, so these are usually trialed one at a time, with a defined review point and realistic expectations about what a supplement can and cannot change.
Treating Identified Infections or Overgrowth
If a pathogen, parasite or fungal overgrowth is identified, treatment with antibacterial, antiparasitic or antifungal medication is prescribed by a clinician, often with follow-up testing to confirm clearance. Not every positive molecular result needs treatment, particularly when the organism detected is not clearly responsible for symptoms.
Modulating Motility and the Gut-Brain Axis
Depending on whether transit appears fast or slow, options may include antidiarrheal or antispasmodic medication, prokinetics, bile acid binders, and behavioral approaches such as gut-directed hypnotherapy, cognitive behavioral therapy and stress management, several of which have evidence in IBS. Symptoms and stool patterns are often tracked between appointments to judge whether a change is working.
Monitoring Progress
Repeat testing is most useful for specific questions, such as confirming that an infection has cleared or tracking inflammation over time. Routine repeat microbiome sequencing is more debatable, because microbial communities fluctuate from day to day and a change on a report does not always correspond to a change in symptoms.
When to Seek Medical Advice
Some symptoms should prompt timely medical assessment rather than a self-directed testing or supplement plan.
- Blood in the stool, or black tarry stools
- Unintentional weight loss
- Fever, severe abdominal pain, or diarrhea that wakes you at night
- Diarrhea lasting more than a few days, or recurring over several weeks
- Signs of dehydration
- Diarrhea that begins after hospital care, travel or a course of antibiotics
- A new change in bowel habit after age 50, or a family history of colorectal cancer or inflammatory bowel disease
These signs do not automatically indicate something serious, but they change which tests are appropriate and how quickly they should be arranged. Discuss persistent or worrying symptoms with a qualified healthcare professional.

Frequently Asked Questions About Stool Tests
Is a stool test as good as a colonoscopy?
They answer different questions and are not interchangeable. A stool test is non-invasive and can indicate that something needs further investigation, but it cannot see the lining of the colon, cannot remove polyps and can miss some lesions. A colonoscopy directly visualizes the colon and allows tissue sampling or polyp removal during the same procedure. When a stool test is positive or symptoms are concerning, colonoscopy is usually the next step.
Can a stool test detect cancer?
Stool tests used for colorectal cancer screening, such as FIT and stool DNA tests, can detect signs that may be associated with cancer or advanced polyps, most often hidden blood or altered DNA. A positive result does not mean cancer is present, and a negative result does not rule it out. These tests are a screening tool rather than diagnostic confirmation, and any positive screening result is followed up with colonoscopy.
What are the three stool tests?
There is no single official list of three, but a common way to group them is: stool culture or molecular panels for infection; inflammation and digestive function markers such as calprotectin, lactoferrin, fecal elastase and stool fat; and occult blood or stool DNA tests used for colorectal cancer screening. Routine stool analysis with microscopy may also be included depending on the laboratory.
How long does it take to get stool test results?
It depends on the test. Occult blood tests and some antigen tests can be reported within hours to a couple of days. A stool culture typically takes around 24 to 72 hours, and longer if an unusual organism needs further identification or antibiotic susceptibility testing. PCR panels are often available within a day. Broader microbiome and metabolomic panels can take one to several weeks because of the sequencing and analysis involved.
What is another name for a stool test?
Stool tests are also called stool sample tests, fecal tests, stool analysis, or by the specific method ordered, such as stool culture, ova and parasite exam, fecal immunochemical test (FIT), fecal occult blood test (FOBT) or stool DNA test.
Key Takeaways
- Stool tests are not interchangeable: culture, molecular panels, antigen tests, occult blood tests, inflammation markers and microbiome sequencing each answer a different question.
- Knowing what a routine stool test detects helps you read a report as a set of signals rather than a verdict.
- Proper sample collection and freshness strongly influence reliability, so follow the instructions supplied with the kit.
- No stool test diagnoses IBS on its own, and microbiome findings describe patterns rather than causes.
- Results are best used to guide dietary, microbial, anti-inflammatory and motility-focused approaches, with treatment decisions made by a qualified clinician.
Find more details about IBS & Motility
You can find more information on the related topics below.
Read more: Stool Test Guide for Diarrhea, IBS and Gut Motility
Your Gut Has a Story. Read It — Then Fix Potential Problems
Full microbiome sequencing + Gut Health Index. Metabolic pathways, diversity, keystone species. Personalized plans available (diet, supplements, diary, recipes). EU lab + Maastricht University spin-off + GDPR-safe.