Understanding Gut Barrier Integrity Markers in Gut Health and Microbiome Tests

SelfDecode Gut Microbiome Testing: What Tests Measure and How to Compare
Gut Barrier Integrity Markers: What Gut Health Tests Measure
The lining of the gut is not a passive tube. It works as a selective barrier that lets nutrients and water through while keeping most bacteria, undigested food particles and larger molecules inside the intestinal lumen. Gut barrier integrity markers are measurable compounds that give an indication of how well that barrier is functioning. They are increasingly included in gut health tests and microbiome panels.
The Gut Barrier Is a Selective System
The barrier is a layered system rather than a single structure:
- A single layer of epithelial cells, called enterocytes, that line the intestine
- Tight junction proteins, including occludin and claudins, which seal the spaces between those cells
- A mucus layer that physically separates microbes from epithelial cells
- Immune components such as secretory IgA and resident immune cells that monitor what crosses the lining
- The gut microbiota, which interacts with all of the above and influences barrier behaviour
When these components work together, the barrier stays selectively permeable. When they are disrupted, permeability can increase, a state often described in everyday language as leaky gut.
Increased Intestinal Permeability: What It Means
Increased intestinal permeability is a measurable phenomenon, but it is also widely misunderstood. Research has associated it with conditions such as irritable bowel syndrome, inflammatory bowel disease, coeliac disease and some metabolic conditions. Association, however, is not the same as causation, and in many cases it is unclear whether altered permeability contributes to a condition or results from it.
This is one reason barrier markers are described as indicators rather than diagnoses. A single elevated value does not confirm a disease, and a normal value does not rule one out.
Why Barrier Markers Are Included in Gut Health Tests
Microbiome sequencing describes which microorganisms are present and in what relative amounts. Barrier markers describe something different: the functional state of the intestinal lining. Combining the two can give a more complete picture than either measurement alone, because the microbiota and the barrier influence each other continuously.
What This Guide Covers
- The main barrier integrity markers measured in gut health testing and what each one reflects
- How stool, blood, urine and biopsy-based tests measure barrier function
- How these markers sit alongside the wider range of gastroenterology tests
- How to interpret results together with microbiome data, including the limits of what they can show
- Practical guidance on preparation, when to seek medical advice, and common questions

Key Gut Barrier Integrity Markers and What They Indicate
Different markers reflect different aspects of barrier function: some show tight junction regulation, some show epithelial cell damage, and others show immune exposure to bacterial components or active inflammation.
Zonulin and Tight Junction Regulation
Zonulin is a protein involved in regulating the tight junctions between intestinal epithelial cells. It has been described as a physiological modulator of permeability, capable of temporarily opening junctions in response to certain stimuli.
Higher zonulin levels have been associated with increased intestinal permeability, and it is one of the most frequently marketed markers in consumer gut health tests, typically measured in blood or stool. It is worth noting that zonulin assays have been debated in the scientific literature, with questions about standardisation and comparability between laboratories. Results should therefore be interpreted with caution and in context rather than as a standalone verdict on gut health.
Occludin, Claudins and Other Tight Junction Proteins
Occludin and claudins are structural proteins that form the tight junction complex itself. Changes in their expression or distribution can destabilise the barrier and alter what passes between cells.
These proteins are usually assessed through tissue biopsies or specialised molecular assays in research settings rather than through routine consumer tests. They are valuable for understanding mechanisms, but they are not yet standard in everyday gut health panels.
Lipopolysaccharide and Lipopolysaccharide-Binding Protein
Lipopolysaccharides are components of the outer membrane of Gram-negative bacteria. Under normal circumstances they remain largely confined to the gut lumen. If the barrier is compromised, small amounts can enter the bloodstream, where they are recognised by the immune system.
LBP is the protein that binds LPS and helps mediate this immune response. Elevated LBP in blood is therefore interpreted as a sign of increased bacterial translocation and greater immune exposure to bacterial components. It is a research and clinical marker rather than a diagnosis in itself.
Intestinal Fatty Acid-Binding Protein
I-FABP, also referred to as FABP2, is an intracellular protein found in the enterocytes lining the intestine. When these cells are damaged, the protein is released into the bloodstream.
This makes it a marker of epithelial cell injury rather than of permeability in the strict sense. Raised levels can indicate that enterocytes are being damaged, which may precede or accompany broader barrier dysfunction.
Calprotectin as a Marker of Intestinal Inflammation
Calprotectin is a protein released mainly by neutrophils and is measured in stool. It is one of the most established markers in gastroenterology, where it is used to help distinguish inflammatory conditions from functional bowel symptoms and to monitor disease activity over time.
Calprotectin does not measure permeability directly. Rather, it reflects inflammation, and inflammation frequently disrupts barrier integrity. In practice it is often used together with barrier and microbiome data rather than in isolation.
Functional Permeability Testing: The Lactulose-to-Mannitol Ratio
Some tests assess permeability functionally rather than by measuring a single protein. In a sugar permeability test, a person drinks a solution containing sugars of different molecular sizes, and the amount recovered in urine over the following hours is measured.
A higher lactulose-to-mannitol ratio suggests that larger molecules are passing between epithelial cells, which is consistent with increased paracellular permeability. This approach is used mainly in research and specialist settings.
Reading Markers Together, Not Individually
No single marker provides a definitive answer about gut barrier function. Zonulin, occludin and claudins relate to junction regulation, I-FABP to cell damage, LBP to bacterial translocation, and calprotectin to inflammation. Each tells part of the story, and the meaningful signal usually comes from patterns across several markers, considered together with symptoms, medical history and reference ranges from the laboratory that performed the test.

SelfDecode Gut Microbiome Testing: What Tests Measure and How to Compare
How Gut Health Tests Measure Barrier Integrity
Barrier markers can be measured from several different sample types, and the choice of test usually depends on the question being asked and whether the test is being used for research, clinical care or general wellbeing interest.
Stool-Based Testing
Stool is the most common sample for non-invasive gut assessment because it can be collected at home and reflects the luminal environment directly. A comprehensive stool analysis may combine:
- Microbial composition and diversity through sequencing
- Faecal calprotectin as an inflammation marker
- Faecal zonulin as a permeability-related marker
- Secretory IgA, digestive enzyme activity and short-chain fatty acid profiles in some panels
Because a single sample captures only a snapshot, some providers recommend repeat testing when results are borderline or symptoms change.
Blood-Based Biomarker Panels
Blood tests can detect markers that have entered circulation, including LBP, zonulin and I-FABP, alongside general inflammatory markers such as high-sensitivity CRP. These panels are useful because they can indicate systemic exposure to bacterial components or ongoing epithelial damage without an invasive procedure, and they allow changes to be tracked over time.
Urine Permeability Tests
Sugar absorption tests using lactulose and mannitol, or similar sugar combinations, assess how readily different sized molecules cross the intestinal lining. They are used mainly in specialist and research contexts and require careful protocol adherence to be meaningful.
Biopsy-Based and Molecular Methods
Tissue sampling during endoscopy or colonoscopy allows direct assessment of tight junction proteins and epithelial structure. Molecular techniques such as quantitative PCR and next-generation sequencing can then examine the expression of genes involved in barrier regulation. These approaches provide the most detailed mechanistic information but are reserved for situations where invasive investigation is justified.
Microbiome Sequencing Alongside Barrier Markers
Many modern gut health tests combine microbiome sequencing with barrier markers to build a broader profile. For example, a low abundance of butyrate-producing bacteria may be reported alongside elevated zonulin or LBP. These combinations are informative for research and for guiding lifestyle discussions, but they describe associations rather than confirmed causes, and they should not be treated as a diagnosis.
Common Gastroenterology Tests and What They Look For
If you are being investigated for persistent digestive symptoms, a clinician may recommend one or more of the following procedures. Barrier marker panels are only one part of this wider picture, and they do not replace standard medical assessment.
- Upper endoscopy, also called gastroscopy, uses a flexible camera passed through the mouth to examine the oesophagus, stomach and duodenum, with the option to take biopsies, for example to investigate coeliac disease, ulcers or H. pylori infection
- Colonoscopy examines the large bowel and the end of the small intestine, allows biopsies and polyp removal, and is central to investigating inflammatory bowel disease and to colorectal cancer screening
- Stool tests include faecal calprotectin for inflammation, faecal immunochemical testing for hidden blood, and culture or PCR testing for infections and parasites
- Breath tests are used for lactose or fructose intolerance, small intestinal bacterial overgrowth and H. pylori detection
- Capsule endoscopy uses a swallowed camera that images areas of the small intestine that standard endoscopes cannot easily reach
- Imaging such as ultrasound, CT and MRI, including specialised small bowel imaging, can look at structure and inflammation
- Blood tests include coeliac serology, full blood count, inflammatory markers, and liver, thyroid and nutrient panels
What These Tests Can and Cannot Do
These investigations are effective at identifying structural disease, active inflammation, infection, malabsorption and some functional disorders. What they generally cannot do is explain every symptom, and no test currently provides a complete picture of an individual microbiome or barrier function. Barrier marker panels add context, particularly when symptoms are persistent but standard tests appear normal, but they are complementary to gastroenterology assessment rather than a substitute for it.
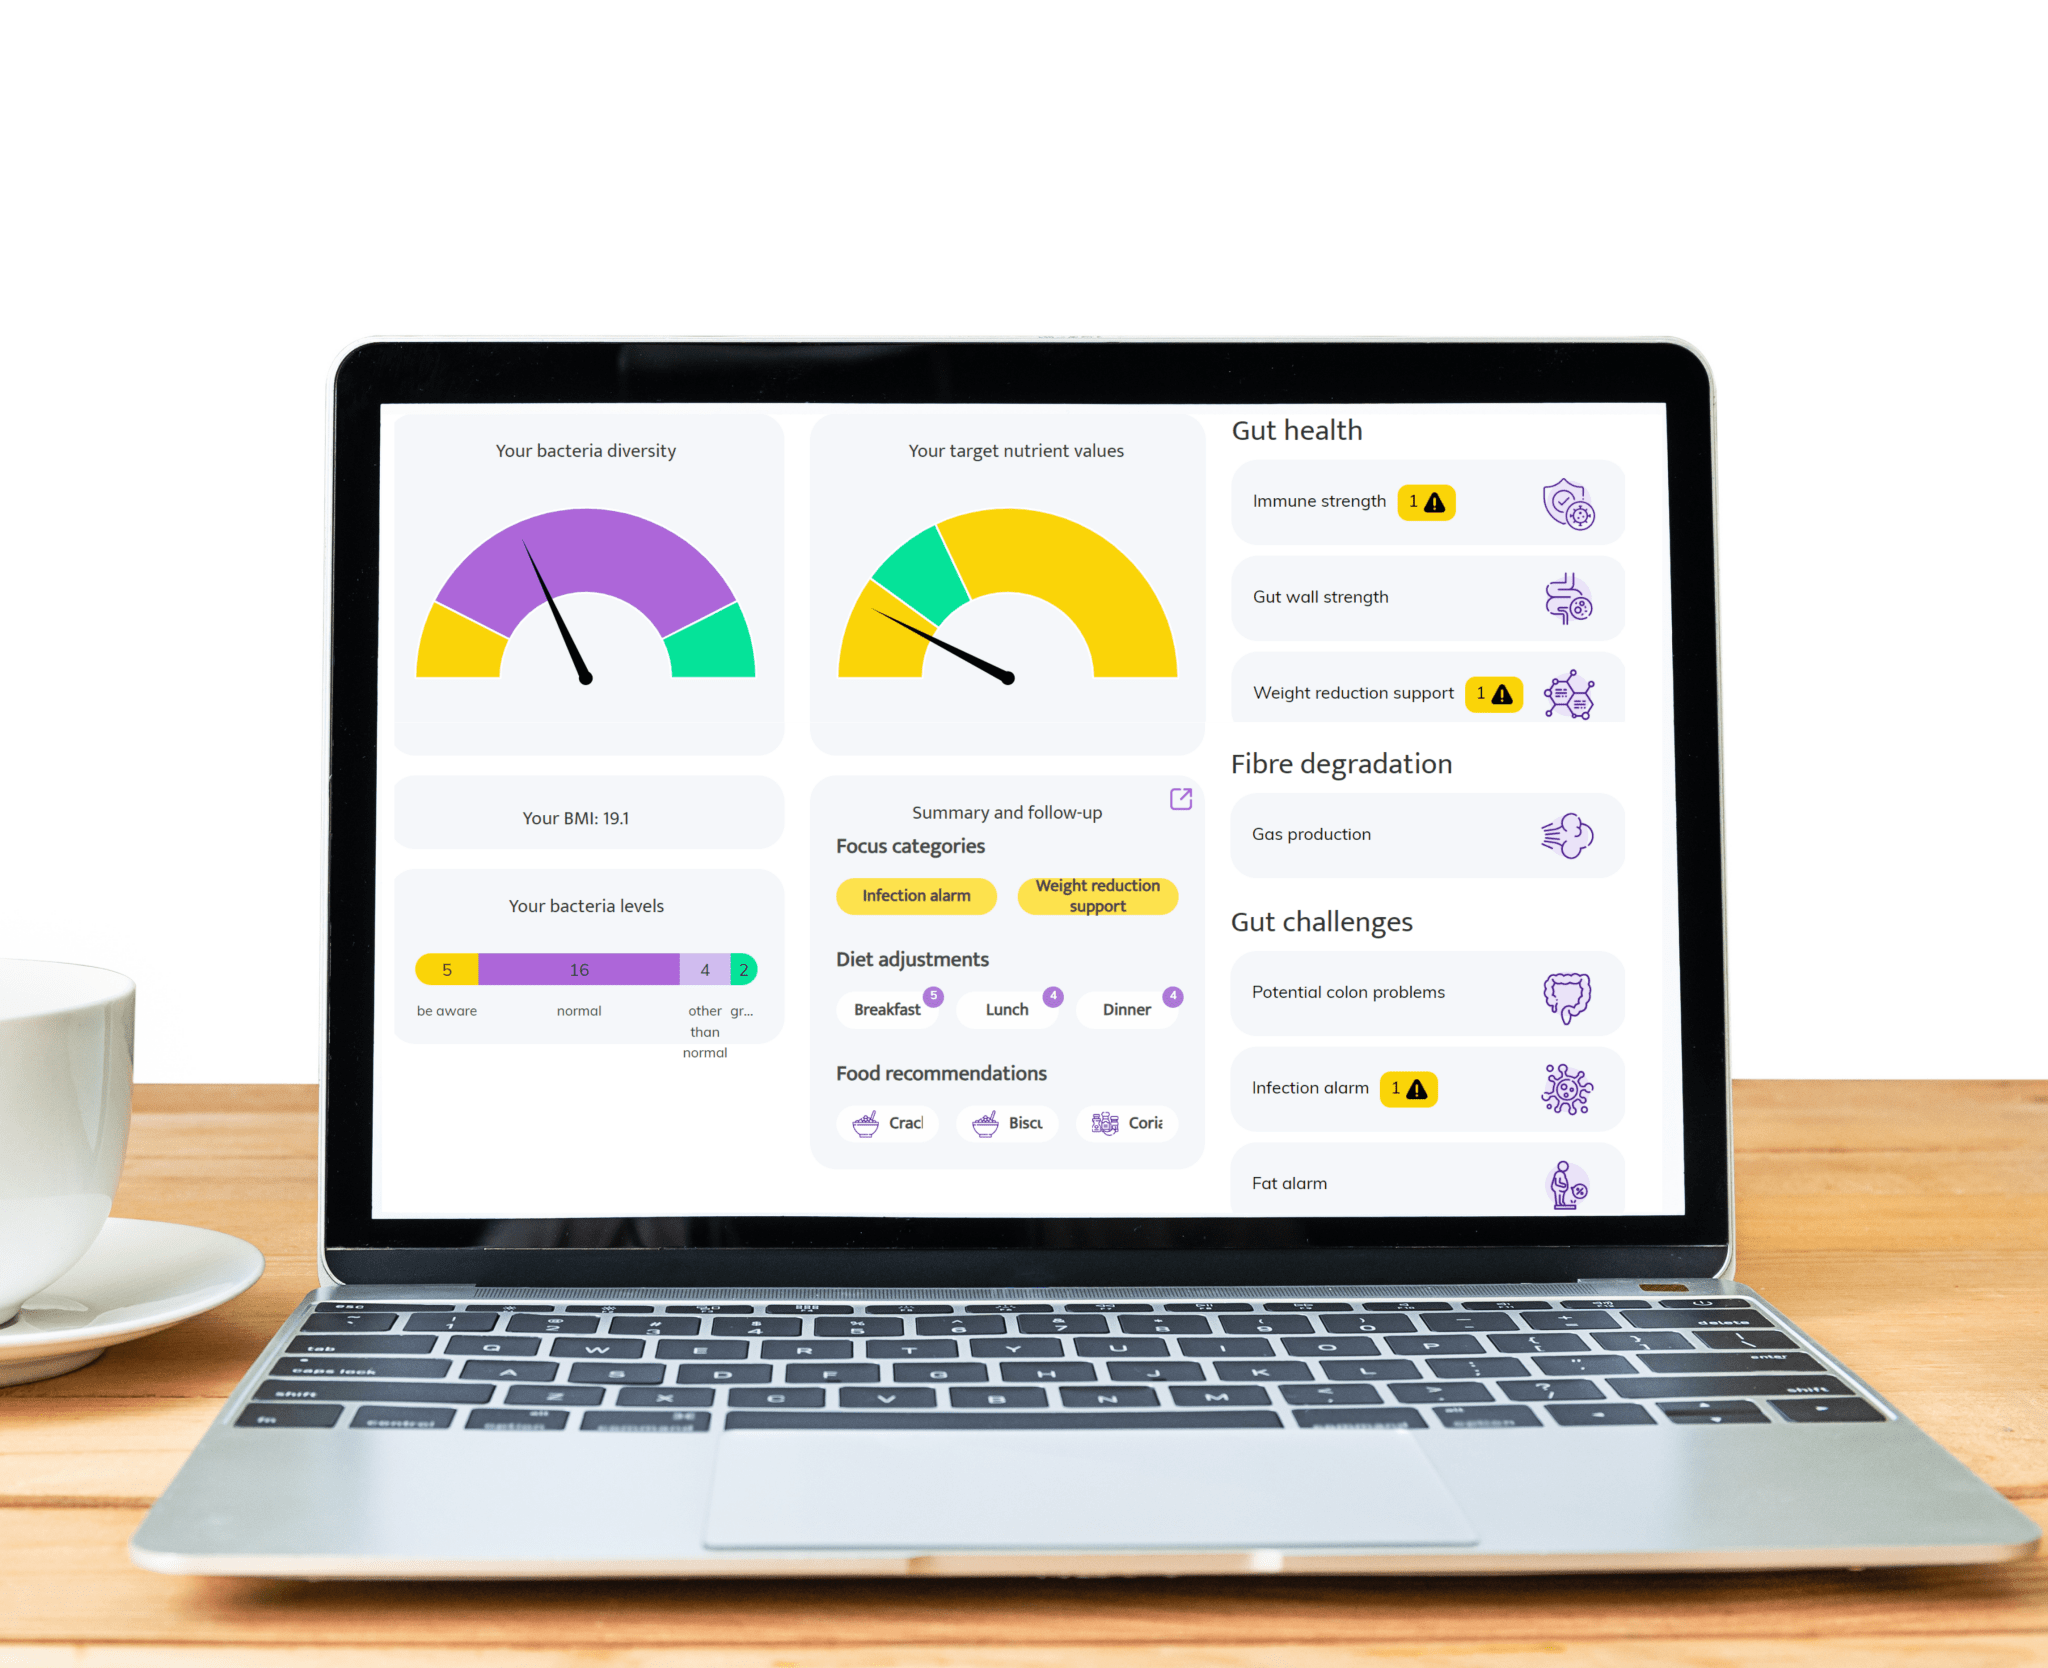
Interpreting Barrier Markers Alongside Microbiome Results
Barrier markers become more useful when they are read together with microbiome data, symptoms and clinical history rather than in isolation.
How the Microbiota Influence the Barrier
Gut bacteria interact with the intestinal lining in several ways. Fermentation of dietary fibre produces short-chain fatty acids such as butyrate, which serve as fuel for colon cells and have been associated with support for mucus production and tight junction function. Microbes also influence bile acid metabolism and help shape immune responses in the gut.
This relationship runs in both directions: the barrier helps determine which microbes and microbial products reach the immune system, and the microbiota in turn influences how the barrier behaves.
Recognising Patterns That Suggest Dysbiosis
Dysbiosis is a broad term for a microbial community that has shifted away from a typically diverse, stable state. There is no single agreed definition or universal healthy microbiome, so the concept is best treated as a pattern rather than a threshold.
Patterns that researchers and clinicians may look at together include low microbial diversity, reduced numbers of butyrate-producing groups, and elevated barrier or inflammatory markers such as LBP, zonulin or calprotectin appearing at the same time. These combined signals can suggest that microbial imbalance and barrier disruption are occurring together, but they do not establish which came first.
What the Hörnberg 2020 Work Added to the Discussion
The 2020 work by Hörnberg and colleagues examined the relationship between the gut microbiome and intestinal barrier integrity. It brought together themes that recur across microbiome barrier integrity research: microbial metabolites, immune signalling and tight junction regulation all interact, and measuring barrier function in humans remains methodologically challenging. The paper did not establish that any single marker or microbiome pattern causes disease. Instead, it supports a cautious interpretation in which microbiome and barrier data are considered together, alongside clinical context.
Inflammation and Autoimmune Conditions
Barrier dysfunction is frequently observed in inflammatory and autoimmune conditions, and markers such as calprotectin, I-FABP and zonulin are used in research to study disease activity and treatment response. In clinical practice, these markers support decisions rather than determine them, and they are always interpreted alongside endoscopy findings, imaging, symptoms and other laboratory results.
The Gut-Brain Axis and Neurodevelopmental Research
The gut and the central nervous system communicate through immune, metabolic and neural pathways, a relationship often described as the gut-brain axis. Research has explored whether differences in gut microbiota and barrier function are relevant to neurodevelopmental conditions such as autism spectrum disorder.
Some studies have reported differences in microbial composition in groups of children with autism spectrum disorder compared with other groups, but findings across studies are inconsistent, sample sizes are often small, and it remains unclear whether any observed differences contribute to, accompany or result from other factors such as diet, medication or environment. Microbiome or barrier testing cannot diagnose autism spectrum disorder or any other neurodevelopmental condition, and no test result should be used to justify delaying or replacing standard developmental assessment and care.
Diet, Lifestyle and Barrier Function
Several everyday factors have been studied in relation to barrier function:
- Fibre-rich diets and fermented foods are associated with short-chain fatty acid production and a more diverse microbiota
- Diets high in ultra-processed foods and alcohol have been linked with increased permeability in some studies
- Chronic stress, poor sleep and long-term use of certain medications such as NSAIDs may affect the intestinal lining
- Regular physical activity has been associated with favourable microbiome and metabolic markers
These findings are largely observational, so they describe tendencies rather than guaranteed effects for any one person. Test results can nonetheless help frame a conversation about diet, sleep and stress with a qualified professional.
Limitations Worth Keeping in Mind
- Assay standardisation varies between laboratories, and this is a known issue for zonulin in particular
- Reference ranges are laboratory-specific and are not always comparable across providers
- Markers fluctuate with diet, illness, medication and time of sampling, so one result is a snapshot rather than a fixed trait
- Elevated markers do not diagnose a disease and normal markers do not exclude one
- Consumer tests differ widely in methodology and in the interpretive support they provide
Because of these limits, barrier and microbiome results are most useful as supporting information in a broader clinical picture.

Practical Guidance, Preparation and Common Questions
When to Speak to a Gastroenterologist
Many digestive symptoms are common and not serious on their own, including occasional bloating, gas or a change in bowel habits. Certain features, however, are worth medical assessment rather than self-monitoring. These can include:
- Blood in the stool, or black, tarry stools
- Unexplained weight loss
- Persistent abdominal pain, particularly at night or waking you from sleep
- Anaemia or unexplained fatigue
- Difficulty swallowing or persistent vomiting
- Fever together with diarrhoea
- A lasting change in bowel habit, especially after the age of 45
- A family history of inflammatory bowel disease or colorectal cancer
If you are unsure whether your symptoms warrant attention, it is reasonable to ask a GP or gastroenterologist. Test results from a consumer panel are not a substitute for that conversation.
Preparing for Gut Health and Gastroenterology Tests
Preparation has a direct effect on how interpretable a result will be:
- Follow fasting and bowel preparation instructions carefully, particularly before endoscopy, colonoscopy or breath tests
- Tell your clinician about all medications and supplements, especially proton pump inhibitors, antibiotics, iron and anti-inflammatories. Never stop a prescribed medicine on your own
- Ask the laboratory or provider whether antibiotics, probiotics or fermented foods should be paused before stool microbiome testing, and for how long. Recommendations vary between providers
- Keep a simple symptom and food diary in the weeks before testing so results can be discussed in context
- Ask in advance who will interpret the results and how they will be used
Comparing Gut Health Test Providers, Including Mool Health
When comparing providers such as Mool Health, Innerbuddies or other gut health testing services, it helps to look at the same practical criteria rather than relying on marketing claims alone. Useful questions include:
- Which sample types are used, and are they collected at home or in a clinic
- Which markers are reported, including whether calprotectin, zonulin, LBP or microbiome sequencing are included
- Whether the laboratory is accredited and how assays are standardised
- What reference ranges are used and whether they are explained clearly
- Whether a qualified professional helps interpret the results
- How your data and sample are stored, used and protected
- Whether the provider makes diagnostic or treatment claims that are not supported by evidence
We cannot verify or rank individual commercial brands, including Mool Health. Questions about whether a specific brand is genuine are best answered by checking these points directly with the provider, reviewing independent information where available, and discussing the results with a clinician if they will affect your care.
Frequently Asked Questions
What is the best test to check gut health?
There is no single best test, because the right choice depends on the question. Stool calprotectin is useful when inflammation is suspected, coeliac serology and blood tests screen for specific conditions, breath tests investigate intolerances and bacterial overgrowth, and endoscopy or colonoscopy assesses structural disease. Microbiome sequencing adds information about microbial composition. In practice, a clinician combines history, examination and selected tests rather than relying on one result.
Is a gut microbiome test worth it?
It can be worthwhile if you want a general picture of your microbial composition and understand the limits. Results are not diagnostic, there is no universally agreed definition of a healthy microbiome, and findings can shift between samples. A microbiome test is most useful when a qualified professional helps interpret it, particularly if you are considering changes to diet or supplements based on the results.
Is Mool Health genuine?
We cannot confirm whether any specific commercial brand is genuine or suitable for you. Instead, assess any provider using the criteria above: laboratory accreditation, marker range, reference ranges, interpretation support and data privacy. If you have a medical concern, seek advice from a qualified clinician rather than relying on a consumer test result alone.
What are the 7 signs of an unhealthy gut?
There is no official list of seven signs, and many digestive symptoms overlap with ordinary changes in diet, stress or routine. Symptoms that may deserve attention include persistent bloating, a lasting change in bowel habit, blood in the stool, unexplained weight loss, fatigue, recurring abdominal pain and symptoms that wake you at night. If these are persistent or worrying, speak to a healthcare professional.
What drink heals your gut?
No single drink heals the gut. Water supports normal digestion and hydration, and some fermented drinks contain live microbes, but evidence for specific gut-healing effects varies and they are not treatments. If you have persistent digestive symptoms, discuss them with a clinician rather than relying on a drink or supplement.
What is the most common test used to diagnose stomach problems?
It depends on the symptoms. Common first-line investigations include blood tests, stool tests such as calprotectin, H. pylori testing and breath tests. Upper endoscopy is commonly used when ulcers, inflammation or structural causes are suspected. Your clinician will choose based on your symptoms, history and examination findings.
What are early signs of gastrointestinal disease?
Early signs can be vague and may include persistent indigestion, nausea, bloating, changes in bowel habit, abdominal pain, fatigue or unintended weight loss. Many of these have harmless explanations, but symptoms that persist, recur or are accompanied by bleeding, anaemia or difficulty swallowing should be assessed medically.
Key Takeaways
- Gut barrier integrity markers describe the functional state of the intestinal lining and are used alongside microbiome data, not instead of it
- Zonulin, occludin and claudins relate to tight junction regulation, I-FABP to epithelial damage, LBP to bacterial translocation, and calprotectin to inflammation
- Results require clinical context, and no single marker diagnoses or excludes a condition
- Common gastroenterology tests such as endoscopy, colonoscopy, stool tests, breath tests and imaging answer different questions than barrier marker panels
- Persistent or red-flag symptoms should be assessed by a medical professional
Barrier marker testing remains an active area of research, and its role in routine care is still evolving. Used carefully and interpreted by someone with the full clinical picture, it can add useful perspective on how the gut lining and the microbiome interact. It works best as one part of a broader assessment rather than as a standalone answer.
Find more details about What Gut Health Tests Measure
You can find more information on the related topics below.
Read more: Gut Barrier Integrity Markers Explained
Your Gut Has a Story. Read It — Then Fix Potential Problems
Full microbiome sequencing + Gut Health Index. Metabolic pathways, diversity, keystone species. Personalized plans available (diet, supplements, diary, recipes). EU lab + Maastricht University spin-off + GDPR-safe.