Calprotectin Levels and Gut Inflammation: How to Interpret Your Results

Gut Microbiome and Inflammation: How Dysbiosis Affects Gut Health
Quick Answer: How to Read a Calprotectin Result
- Below 50 µg/g: generally considered normal, with a low likelihood of significant intestinal inflammation.
- 50–200 µg/g: borderline; repeat testing or further assessment may be appropriate depending on symptoms and history.
- Above 200 µg/g: often considered elevated and usually prompts medical follow-up.
- No single cut-off confirms or excludes a specific disease on its own.
Calprotectin and Gut Inflammation: What the Test Shows
Calprotectin is a protein released mainly by neutrophils, a type of immune cell. It can be measured in stool, where higher levels generally suggest more neutrophil activity in the gastrointestinal tract. Fecal calprotectin is used as a non-invasive marker of possible intestinal inflammation, not as a diagnosis on its own.
What Is Calprotectin?
Calprotectin is made up of two S100 proteins, S100A8 and S100A9. When neutrophils are activated or break down, calprotectin is released into the gut. It can bind metals such as zinc and manganese, which may help limit bacterial growth as part of the innate immune response.
Why Fecal Calprotectin Is Measured
Stool calprotectin testing can help:
- Assess whether gut symptoms may have an inflammatory component.
- Support decisions about who may need further tests such as endoscopy.
- Monitor disease activity in inflammatory bowel disease (IBD).
- Help distinguish inflammatory conditions from non-inflammatory conditions such as irritable bowel syndrome (IBS) when used with clinical assessment.
How to Prepare for a Fecal Calprotectin Test
In most cases, no special preparation is needed. You collect a small stool sample at home or in a clinic, following the instructions provided by the laboratory. Tell your clinician about recent infections, antibiotics, NSAID use and any medicines that may affect the result. Avoid collecting the sample during a menstrual period if there is a risk of blood contamination, unless your clinician advises otherwise.
Calprotectin Level Ranges: What Is Considered Concerning?
Reference ranges vary by laboratory and population. A widely used interpretation guide is:
- Below 50 µg/g: generally considered normal, with a low likelihood of significant intestinal inflammation.
- 50–200 µg/g: borderline; repeat testing or further evaluation may be appropriate depending on symptoms and history.
- Above 200 µg/g: often considered elevated and may indicate active inflammation that needs medical follow-up.
A level above 200 µg/g is often the point at which clinicians become more concerned, but no single cut-off rules inflammation in or out. Results should always be interpreted with symptoms, medical history, medications and other test findings.
Why Cut-offs Differ Between Laboratories
- Laboratories use different assays, antibodies and calibration standards.
- Reference ranges are usually based on the population that was originally tested.
- Some guidance applies different thresholds for adults and children.
- Borderline results are often repeated rather than acted on immediately.
What an Abnormal Result Does Not Mean
An elevated calprotectin level does not confirm IBD, cancer or any specific disease. It can also be raised by infections, NSAID use and other gut conditions. A normal result does not completely rule out inflammation either. Calprotectin is one piece of a broader clinical picture.

Gut Symptoms and Conditions Linked to Intestinal Inflammation
Calprotectin is often requested when gut symptoms persist or when a clinician needs to assess whether inflammation may be present. Many digestive symptoms overlap across different conditions, so the test result is most useful when combined with a full assessment.
Symptoms That May Prompt Calprotectin Testing
- Persistent or recurring diarrhea
- Abdominal pain or cramping
- Blood or mucus in the stool
- Urgency or a feeling of incomplete emptying
- Unexplained weight loss, fatigue or anemia
- Fever or night sweats in some cases
These symptoms can occur in IBD, infections, IBS and other conditions. Their presence alone does not indicate a specific diagnosis.
Inflammatory Bowel Disease (IBD)
In Crohn's disease and ulcerative colitis, fecal calprotectin often rises during active inflammation and tends to fall when inflammation is controlled. It can be used alongside symptoms, laboratory tests and imaging to support disease monitoring. A single result cannot confirm the diagnosis or replace endoscopy and biopsy when these are clinically indicated.
Differentiating IBD from IBS
IBS can cause similar symptoms to IBD but is not typically associated with mucosal inflammation. Fecal calprotectin levels are generally normal in IBS. This can help clinicians decide whether invasive testing is necessary, although clinical judgment remains essential.
Conditions Associated With Elevated Calprotectin Beyond IBD
High calprotectin is not specific to IBD. Other situations that can raise levels include:
- Gut infections, including infectious gastroenteritis
- Celiac disease, particularly when the small intestine is actively inflamed
- NSAID-related injury to the intestinal lining
- Diverticular inflammation
- Colorectal cancer
- Other immune-mediated and autoimmune-related gut conditions
Calprotectin cannot identify one particular autoimmune disease or confirm an autoimmune diagnosis. Because elevated levels are not specific to a single condition, the result should always be interpreted in context.
Calprotectin and Celiac Disease
Some people with active, untreated celiac disease have elevated fecal calprotectin, while others have normal levels. Calprotectin is not used to diagnose celiac disease; diagnosis typically relies on specific blood antibodies and, when indicated, a small bowel biopsy.
Monitoring Disease Activity and Relapse
In people with known IBD, rising calprotectin levels may occur before symptoms worsen. This has made the test useful for monitoring disease activity and supporting timely follow-up. It does not replace regular clinical review or recommended endoscopic assessment.

Gut Microbiome and Inflammation: How Dysbiosis Affects Gut Health
Calprotectin and the Gut Microbiome
The gut microbiome is involved in immune regulation and intestinal balance. Research suggests that interactions between gut microbes, immune cells and inflammatory markers such as calprotectin may contribute to digestive health and disease, although the relationship is complex.
Dysbiosis and Inflammation
Changes in the gut microbial community, often called dysbiosis, have been associated with IBD and other inflammatory conditions. Dysbiosis may influence immune activation and neutrophil recruitment, which can be reflected in higher calprotectin levels. However, association does not prove that dysbiosis directly causes inflammation in every case.
How Calprotectin May Shape Microbial Communities
Calprotectin can restrict the availability of metals that some bacteria need for growth. This may affect both harmful and beneficial microbes. Some pathogens have adapted to survive in low-metal conditions, while other bacteria may be more sensitive. The net effect on the microbiome is likely to depend on many factors, including diet, medications and the underlying condition.
Combining Microbiome Testing With Calprotectin
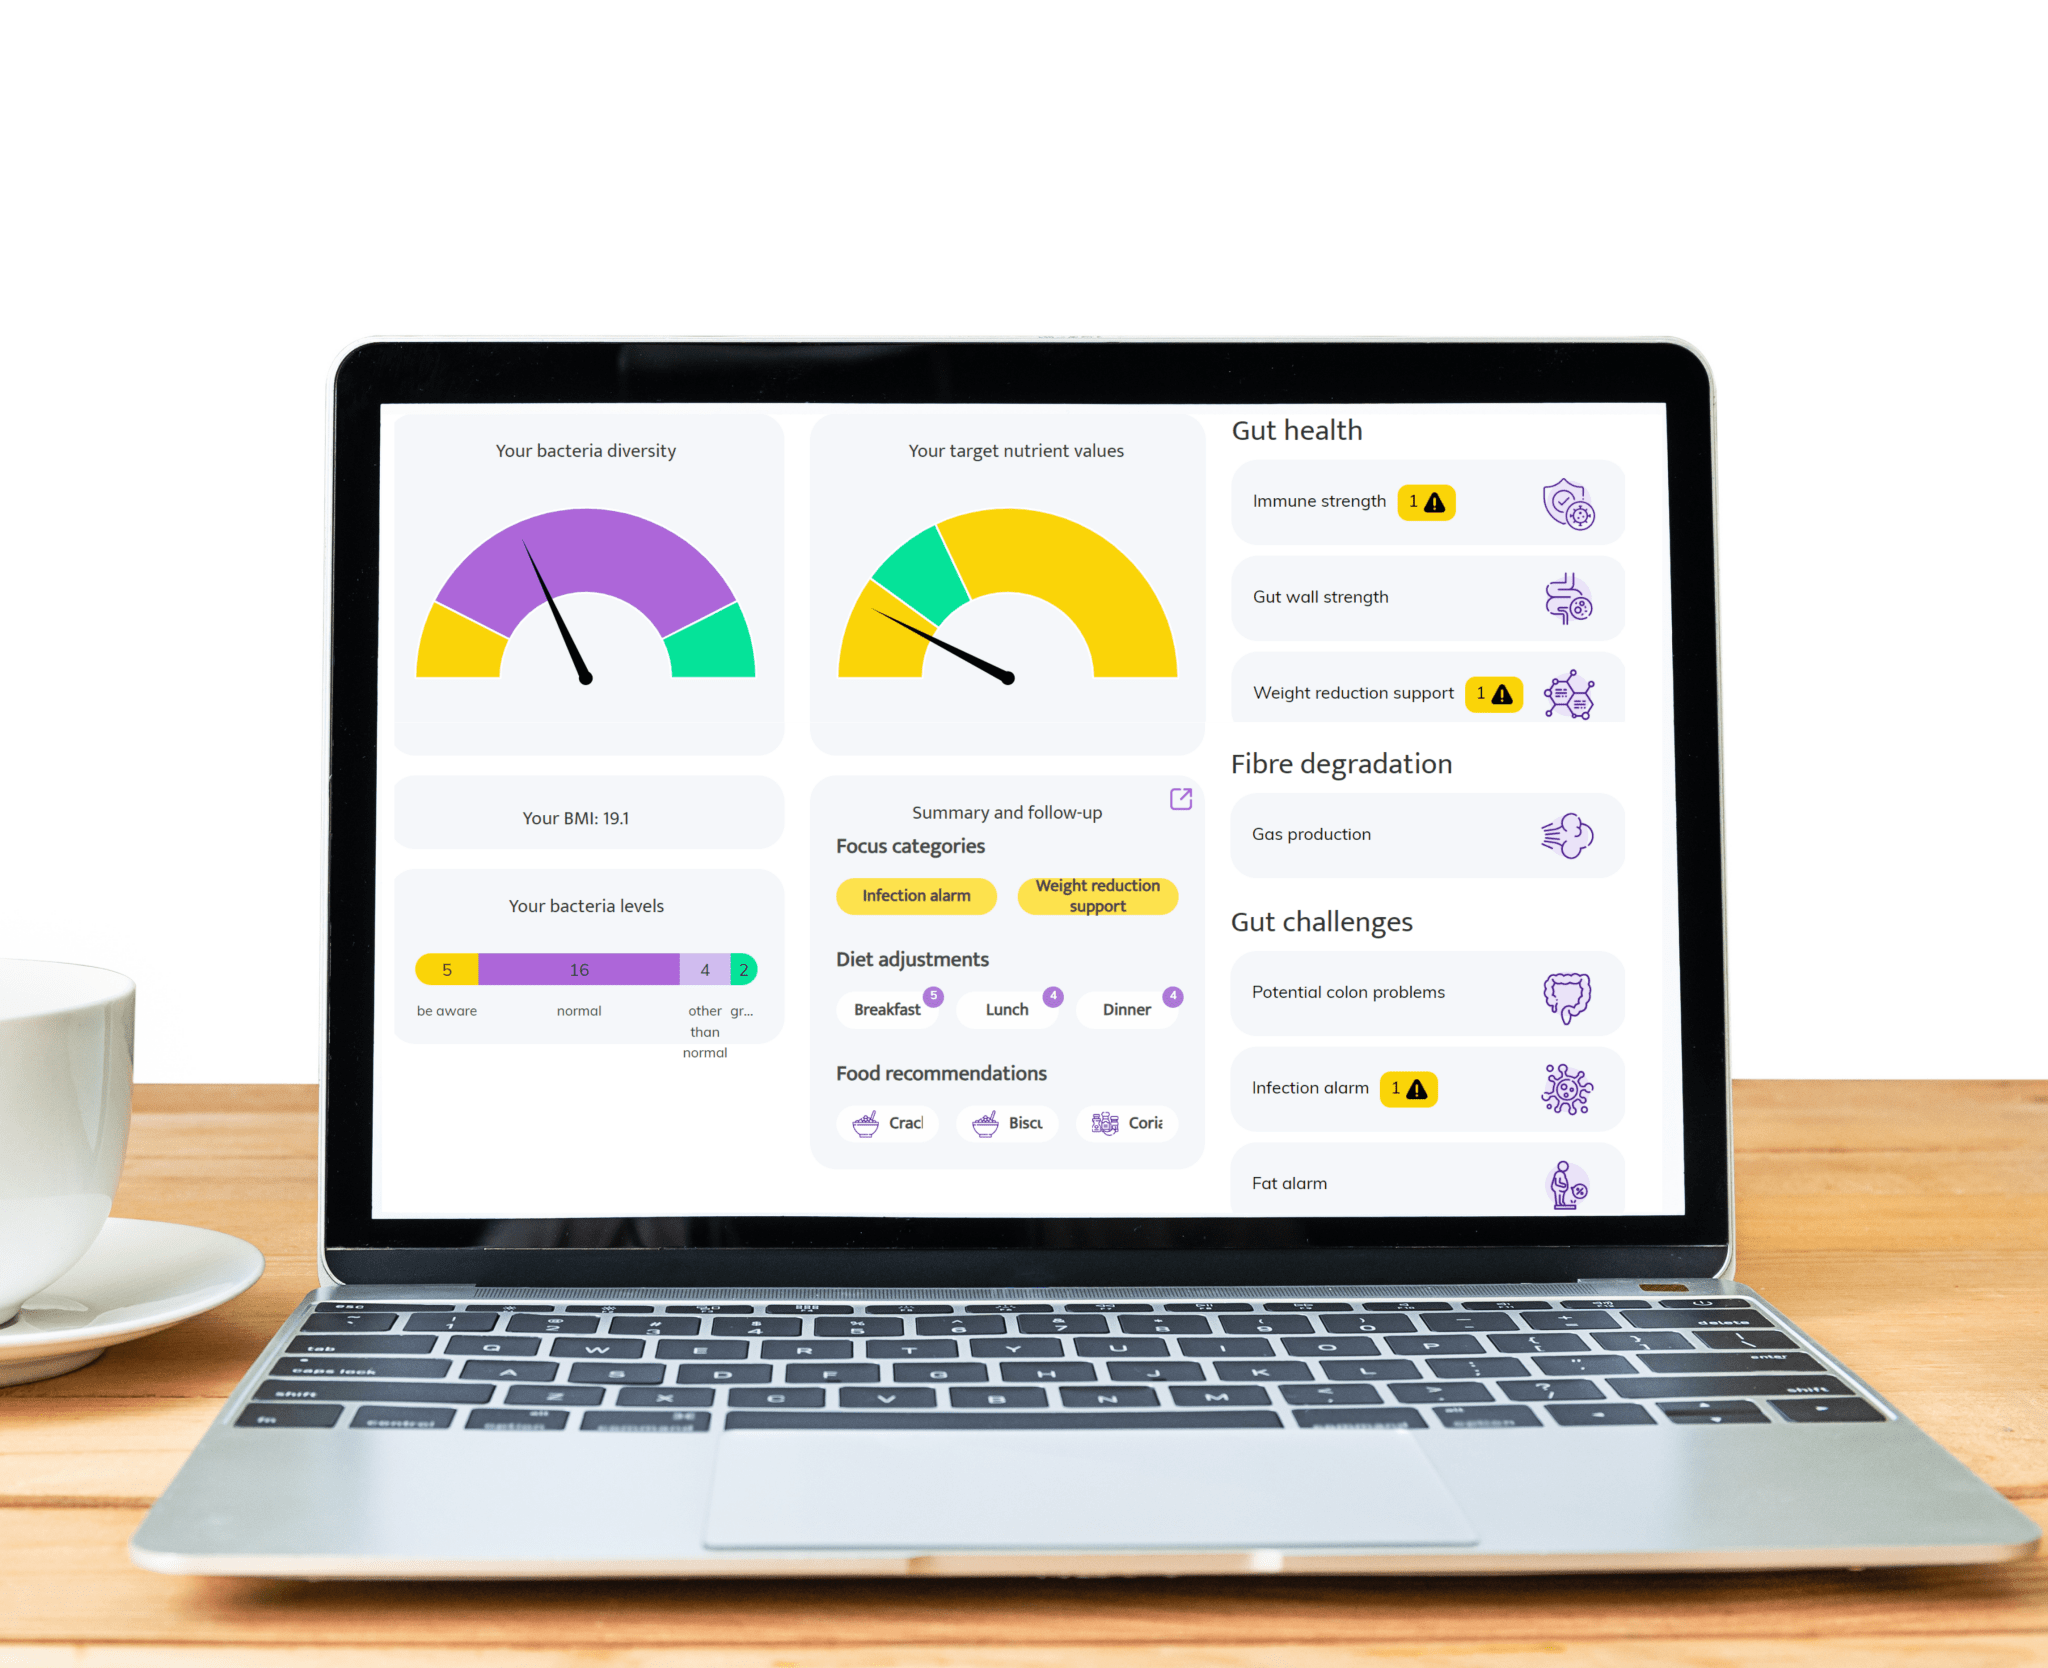
Microbiome testing and calprotectin measure different things. Calprotectin reflects neutrophil activity and possible inflammation; microbiome testing describes the composition or functional potential of the microbial community. Used together, they may provide a broader view of gut health, but current evidence does not support using either test alone to diagnose or exclude specific diseases.
Diet, Stress and Other Lifestyle Factors
Diet quality, sleep and stress management are often discussed as ways to support general gut wellbeing, and some people report fewer digestive symptoms when they work on these areas. Evidence that any single lifestyle change lowers fecal calprotectin is limited, and no diet or supplement is proven to normalise calprotectin or to replace medical treatment. If you are considering dietary changes alongside medical care, discuss them with your clinician or a registered dietitian, particularly if you have IBD or another diagnosed condition.
Therapeutic Approaches Under Study
Approaches such as probiotics, prebiotics, dietary interventions and fecal microbiota transplantation are being studied for their effects on the microbiome and inflammation. Some may influence calprotectin in certain clinical settings, but no single intervention is proven to normalise calprotectin or treat IBD on its own. Treatment should be guided by a qualified clinician.
Clinical Applications and Limitations of Calprotectin Testing
Fecal calprotectin is most useful when it is ordered for a clear clinical question and interpreted alongside other information. It can support care, but it also has important limitations.
When Doctors Order Calprotectin Testing
Calprotectin may be ordered when someone has persistent gut symptoms, when IBD is being monitored, or when a clinician wants to assess whether inflammation is likely before recommending invasive tests. It is not a routine test for every digestive complaint, and it is not a substitute for a full medical evaluation.
Advantages of Calprotectin Testing
- Non-invasive and relatively simple to collect.
- Useful for assessing possible intestinal inflammation.
- Can help triage patients before procedures such as colonoscopy.
- Supports monitoring of IBD activity and treatment response.
- Can make IBS less likely when inflammation is a concern, within the wider clinical picture.
Limitations and Considerations
- Calprotectin is not disease-specific.
- Reference ranges and cut-offs can differ between laboratories.
- Levels may be elevated by infections, NSAIDs and other gut conditions.
- Some people with IBD may have normal or only mildly elevated levels, especially in remission or with limited disease.
- A single result does not replace medical history, physical examination, endoscopy, imaging or biopsy.
- Sample timing, storage and laboratory methods may affect results.
Calprotectin Compared With Other Tests
Calprotectin is one of several tools used to assess gut inflammation. Blood markers such as CRP can also rise with inflammation but are not specific to the gut. Stool cultures can identify infections. Endoscopy and biopsy can directly examine and sample the intestinal lining. Microbiome testing describes microbial composition rather than inflammation. No single test answers every question, so clinicians often combine results.
What to Do After an Abnormal Calprotectin Result
- Ask which reference range the laboratory used, so you know what your number is being compared with.
- Note any recent infections, antibiotic or NSAID use, and current medicines, since these can influence the result.
- Discuss your symptoms, their duration and any changes in bowel habits with your clinician.
- Expect that a borderline result may be repeated before further tests are arranged.
- Ask whether additional investigations, such as stool cultures, blood tests, imaging or endoscopy, are appropriate in your situation.
- Do not use a calprotectin result to self-diagnose or to start or stop treatment without medical advice.
Seek prompt medical attention for severe or worsening symptoms such as heavy rectal bleeding, high fever or intense abdominal pain rather than waiting for a routine appointment.
When to See a Specialist
A referral to a gastroenterologist is usually considered when symptoms persist despite initial assessment, when calprotectin is clearly elevated, when IBD is suspected or already diagnosed, or when anemia, weight loss or blood in the stool are present. The decision depends on your overall clinical picture, not on the calprotectin value alone.
Integration Into Clinical Practice
Calprotectin results are most helpful when combined with a person's symptoms, examination findings and other investigations. This integrated approach supports more personalised decisions about monitoring, treatment and the need for invasive testing.

What Research Is Exploring
Research into calprotectin and gut health continues to develop. Scientists are studying whether combining calprotectin with other stool markers, such as lactoferrin and selected cytokines, can improve diagnostic accuracy. Point-of-care tests may make monitoring easier in some settings, and machine learning approaches are being explored to identify patterns in laboratory and microbiome data. These areas remain investigational and should not replace standard clinical care.
Frequently Asked Questions About Calprotectin
What level of calprotectin is concerning?
Many laboratories treat results below 50 µg/g as normal, 50–200 µg/g as borderline, and above 200 µg/g as elevated. A result above 200 µg/g usually prompts medical follow-up, but what counts as concerning depends on your symptoms, history and the range used by your laboratory. A single number is rarely meaningful on its own.
Can you have high calprotectin but no IBD?
Yes. High calprotectin can occur with gut infections, celiac disease, NSAID-related injury, diverticular inflammation, colorectal cancer and other conditions. An elevated result does not confirm IBD by itself and should be reviewed with a clinician.
What autoimmune disease causes high calprotectin?
No single autoimmune disease causes high calprotectin. Elevated levels are not specific to one condition. They can occur in immune-mediated conditions such as IBD and may be associated with autoimmune-related conditions such as celiac disease, but the test cannot identify a particular autoimmune disease.
What are the calprotectin levels associated with celiac disease?
Levels vary. Some people with active celiac disease may have elevated fecal calprotectin, while others have normal levels. Calprotectin is not used to diagnose celiac disease; celiac testing typically involves specific blood antibodies and, when indicated, a small bowel biopsy.
Can calprotectin be normal in IBD?
Yes. Some people with IBD have normal or only mildly elevated calprotectin, particularly during remission or when inflammation is limited. If symptoms continue, further evaluation may still be needed.
Key Takeaways
Fecal calprotectin is a practical, non-invasive marker that can offer useful information about possible intestinal inflammation. It is especially helpful for triage and monitoring when it is interpreted with symptoms, medical history and other tests. Its limits matter: elevated results are not diagnosis-specific, and normal results do not exclude all disease. Microbiome testing may add context, but its relationship with calprotectin is still an active area of research. If you have persistent gut symptoms or an abnormal calprotectin result, seek personalised medical advice.
Find more details about Gut Inflammation
You can find more information on the related topics below.
Read more: Interpreting Calprotectin Levels, Gut Inflammation and Microbiome Signals
Your Gut Has a Story. Read It — Then Fix Potential Problems
Full microbiome sequencing + Gut Health Index. Metabolic pathways, diversity, keystone species. Personalized plans available (diet, supplements, diary, recipes). EU lab + Maastricht University spin-off + GDPR-safe.